
For someone living with Type 1 diabetes, one of the most frightening emergencies can happen when they’re unable to help themselves.
Blood sugar begins falling.
Then it falls further.
Confusion sets in. A person may become unable to eat or drink. Severe hypoglycemia can progress to seizures, unconsciousness and, without treatment, death.
The standard emergency rescue is glucagon, a hormone that tells the liver to release stored glucose into the bloodstream.
But glucagon only helps if someone can actually administer it.
What happens when a person is asleep, unconscious or a young child who can’t recognize what’s happening?
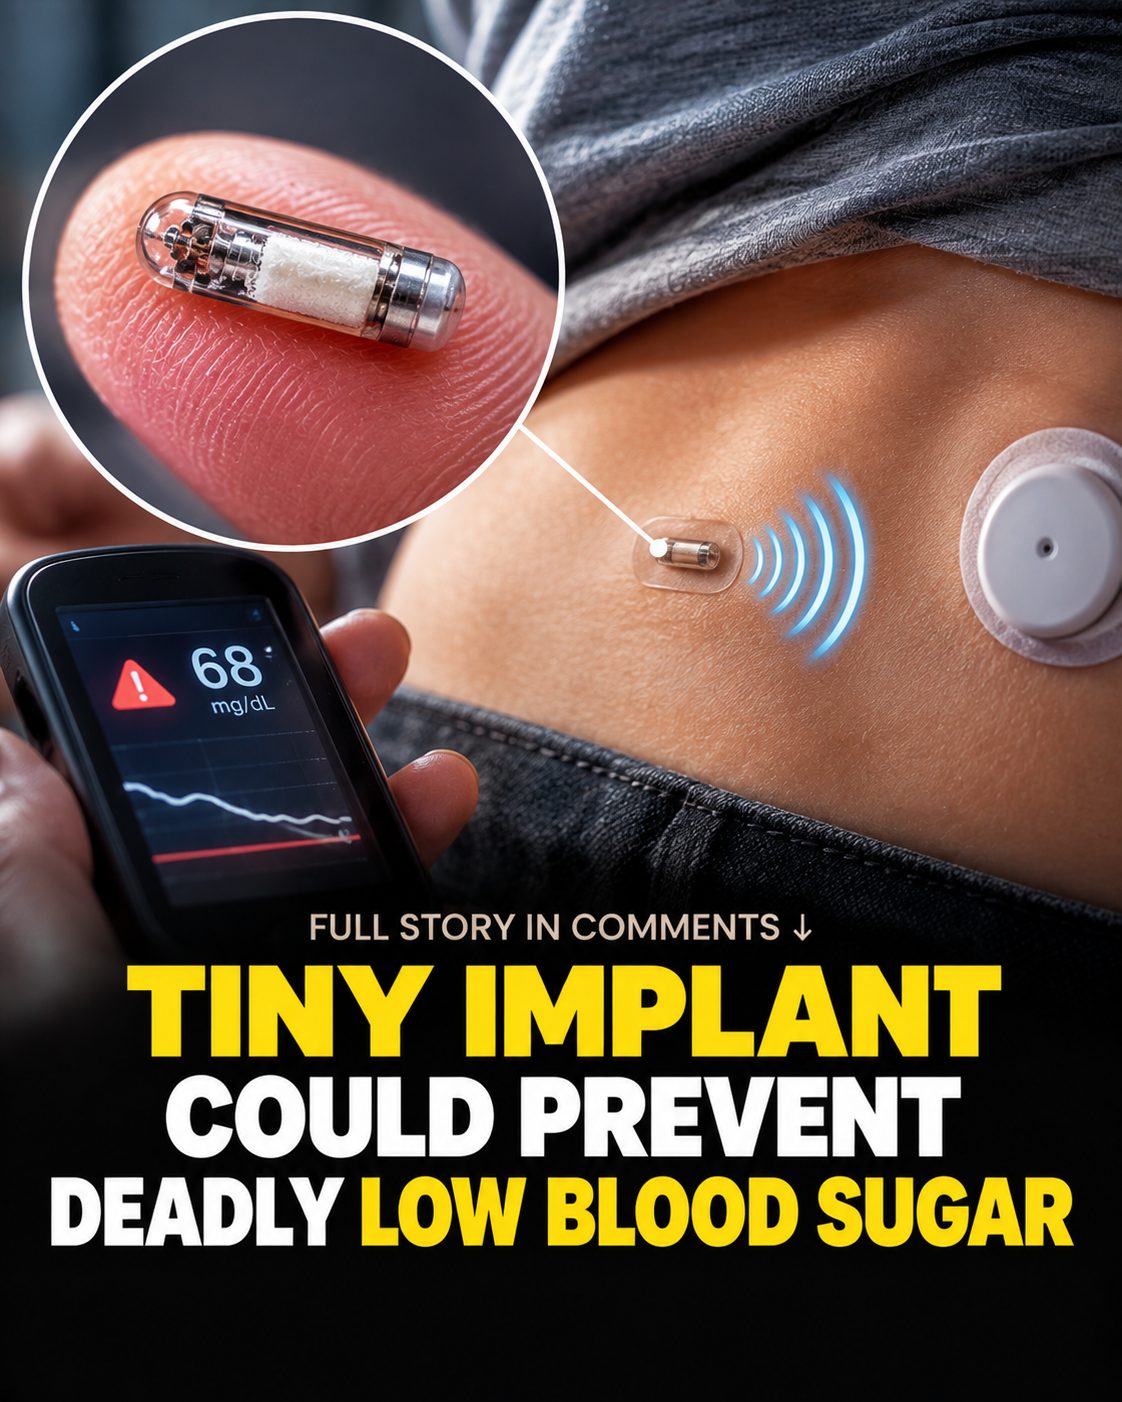
Engineers at MIT have developed an experimental implant designed specifically for that vulnerable moment: a tiny reservoir placed beneath the skin that stores powdered glucagon and can release it wirelessly when blood glucose becomes dangerously low. MIT News
Even more intriguing, researchers envision connecting it directly to a continuous glucose monitor.
In that configuration, the system could potentially recognize severe hypoglycemia and release glucagon automatically—without the patient waking up or another person giving an injection. MIT News
The Device Is Smaller Than You Might Expect
The implant is tiny.
MIT describes it as approximately the size of a U.S. quarter, while the research paper reports a volume below 3 cubic centimeters and a weight under 2 grams. MIT News
It’s designed to sit underneath the skin.
Inside is a small 3D-printed polymer reservoir containing glucagon.
But there’s an unusual feature:
the glucagon isn’t stored as a liquid.
It’s stored as a dry powder.
That solves one of the biggest engineering problems the researchers faced.
Why Powdered Glucagon Matters
Glucagon is a peptide hormone, and storing peptide drugs inside the body for extended periods can be difficult.
Liquid formulations can lose stability over time.
That’s particularly troublesome for an emergency implant.
Imagine having a device underneath your skin for months waiting for an emergency—only to discover that its medication has degraded by the time you actually need it.
Dry formulations can remain stable considerably longer.
So the MIT researchers developed a system that stores glucagon in a particulate powdered form, protected inside the implant until the moment it’s needed. Nature
Once released underneath the skin, the particles encounter the body’s interstitial fluid and dissolve.
Now they can enter circulation and begin raising blood glucose.
How Does a Sealed Implant Suddenly Open?
This may be the cleverest part.
The reservoir is sealed by a shape-memory alloy made from nickel and titanium.
Shape-memory materials can be engineered to change configuration when they reach a particular temperature.
The researchers programmed this material to curl from a flat shape into a U shape when heated to approximately 40°C.
The implant also contains an antenna capable of receiving a wireless radiofrequency signal.
When activated, that signal generates a small electrical current.
The current heats the shape-memory alloy.
It curls.
The reservoir opens and releases the glucagon. MIT News
No syringe.
No button physically attached to the implant.
And potentially, no conscious action from the patient.
It Could Be Activated Two Ways
The simplest version would allow a person or caregiver to trigger the implant remotely.
But researchers have a more ambitious possibility in mind.
Because the device can receive wireless signals, it could communicate with the continuous glucose monitors (CGMs) already used by many people with Type 1 diabetes.
Imagine the sequence:
CGM detects dangerously low glucose → signal reaches implant → glucagon is released → glucose begins rising.
MIT researcher Siddharth Krishnan explained that one advantage of this kind of digital drug-delivery technology is its ability to communicate with sensors. MIT News
That could transform the implant from an emergency medication someone has to remember to use into an automated safety system.
Nighttime Is Exactly Where This Could Matter
Continuous glucose monitors already provide alarms when glucose becomes dangerously low.
For many people, that’s enormously valuable.
But an alarm still depends on someone responding.
During sleep, a person may not hear it.
Someone experiencing severe hypoglycemia may also become confused or unconscious before they’re capable of treating themselves.
MIT’s Daniel Anderson specifically identified nighttime hypoglycemia as one of the motivations for developing the device. MIT News
An automated implant could theoretically go one step beyond:
instead of only sounding the alarm, it could administer the rescue medication.
For parents of young children with Type 1 diabetes, that possibility is especially compelling.
Researchers Tested It in Diabetic Mice
So far, this isn’t a human treatment.
The crucial experiments were performed in diabetic mice.
Researchers implanted the devices and then allowed the animals’ blood glucose to fall.
They remotely activated the glucagon reservoir.
The response came quickly.
Within less than 10 minutes, glucose levels began leveling off and remained in the normal range rather than continuing into severe hypoglycemia. MIT News
The peer-reviewed paper reports rapid therapeutic effects from the wireless delivery of dry glucagon and successful rescue from hypoglycemia in diabetic mice. Nature
That’s an encouraging proof of concept.
But mice aren’t people, and human testing will be necessary before anyone knows whether the system is sufficiently reliable and safe for routine use.
Scar Tissue Presented Another Challenge
Putting something underneath the skin creates a predictable biological response.
The body recognizes a foreign object.
Over time, fibrotic tissue can form around an implant.
That creates a potential problem for drug delivery.
If the implant becomes encapsulated by tissue, can glucagon still escape quickly enough during an emergency?
Researchers specifically designed the device to actively eject the powdered medication rather than simply allowing it to diffuse slowly outward.
The experiments showed that it could deliver medication across fibrotic tissue that developed around the implant. Nature
For an emergency device, that’s critical.
A rescue treatment that works beautifully the week after implantation but fails six months later wouldn’t provide much reassurance.
One Implant Could Hold Multiple Rescue Doses
The researchers built versions capable of holding either one or four glucagon doses. MIT News
That opens the possibility of leaving an implant in place for an extended period while retaining several emergency interventions.
In the published experiments, implants were kept in animals for up to four weeks.
The researchers said their next goal was to extend that period substantially—potentially to at least one year. MIT News
A year-long device would be a very different proposition from something that needs frequent surgical replacement.
But achieving that lifespan still needs to be demonstrated.
Why Glucagon Raises Blood Sugar So Quickly
Insulin and glucagon essentially push glucose regulation in opposite directions.
Insulin helps lower blood glucose by facilitating glucose uptake and storage.
Glucagon raises it.
When glucagon reaches the liver, it signals the liver to release stored glucose into circulation.
That’s why glucagon is used as an emergency treatment for severe hypoglycemia.
Modern rescue glucagon products have already made administration easier than the older kits that required mixing medication before injection.
But every external rescue medication shares one fundamental limitation:
someone still needs to administer it.
An implant could potentially eliminate that final step.
This Isn’t an Artificial Pancreas
There’s an important distinction.
The MIT device isn’t intended to replace ordinary insulin therapy or continuously control glucose throughout the day.
Think of it more like an implanted emergency kit.
Most of the time, it does nothing.
It sits beneath the skin holding a stable rescue medication.
Only when glucose reaches a dangerous threshold would the drug need to be released.
And that simplicity could be an advantage.
The system doesn’t need to perfectly reproduce the pancreas every minute of every day.
It needs to work reliably during the moments when failure could become an emergency.
The Technology Could Go Beyond Diabetes
The researchers also loaded the device with another famous emergency medication:
epinephrine.
Epinephrine is used to treat severe allergic reactions such as anaphylaxis and has other emergency medical applications.
After researchers triggered powdered epinephrine release in animals, blood levels rose within about 10 minutes and heart rate increased as expected. MIT News
That suggests the underlying technology isn’t really a “glucagon implant.”
It’s a platform for storing stable powdered emergency medications inside the body and releasing them wirelessly when needed.
In principle, future versions could potentially be adapted for other situations where minutes matter.
Imagine an Implant Talking Directly to a Sensor
This is where the broader idea becomes fascinating.
Wearable sensors are becoming increasingly capable of detecting changes inside the body.
But most sensors simply provide information:
something is wrong.
The MIT approach potentially closes the loop.
A sensor detects the problem.
Software interprets the signal.
The implant delivers the medication.
Detection becomes intervention.
For diabetes, that’s particularly logical because continuous glucose monitoring already provides the necessary real-time measurement.
The missing piece is an emergency drug-delivery system capable of responding.
But We’re Not There Yet
The device remains experimental.
It hasn’t been demonstrated as an approved treatment for people with Type 1 diabetes.
Researchers still need to answer major questions involving:
long-term biocompatibility,
reliability after months inside the body,
wireless activation,
drug stability,
dosing accuracy,
false triggers,
infection risk,
and replacement procedures.
An automatic system would also need extremely robust safeguards.
If an implant is allowed to administer medication without human confirmation, the threshold for reliability becomes extraordinarily high.
You don’t want a rescue device failing to activate.
You also don’t want it activating when it shouldn’t.
Those engineering problems matter just as much as whether the mechanism works in mice.
MIT Is Exploring Another Implant for Diabetes Too
Interestingly, this isn’t MIT’s only attempt to create implantable technology for Type 1 diabetes.
In March 2026, MIT researchers reported progress on a different device containing insulin-producing pancreatic islet cells, combined with an oxygen-generating system designed to keep those cells alive. In animal studies, the cells survived and produced enough insulin to control blood glucose for at least 90 days. MIT News
The two technologies address opposite sides of glucose control.
One aims to provide insulin to prevent glucose from becoming too high.
The glucagon device provides an emergency defense against glucose becoming dangerously low.
Neither is ready to replace today’s established treatments, but together they illustrate how diabetes technology is gradually moving toward systems that do more of the body’s glucose regulation automatically.
The Fear This Device Is Really Trying to Treat
Severe hypoglycemia isn’t only dangerous when it occurs.
The possibility of it occurring can affect everyday life.
Parents may worry about a child’s glucose throughout the night.
People may deliberately allow their glucose to run somewhat higher because they’re frightened of going too low.
Someone who has experienced severe hypoglycemia once may become particularly anxious about another episode.
And some people develop hypoglycemia unawareness, meaning the usual warning symptoms become less noticeable.
Anderson said part of the team’s goal was therefore not merely preventing emergencies but reducing the fear of hypoglycemia experienced by patients and their families. MIT News
That’s perhaps the most interesting way to think about the device.
Most of the time, you’d ideally forget it was there.
It would simply wait.
And if glucose ever dropped dangerously low—perhaps at 2 AM, when the person wearing it couldn’t respond—the implant could potentially do what an emergency injection normally requires another human being to do:
recognize the danger, release glucagon and give the body a chance to bring blood sugar back up.
For now, that has been demonstrated in animals rather than people.
But if the technology survives the long journey from laboratory prototype to reliable human implant, it could turn one of Type 1 diabetes’s most frightening emergencies into something the body carries its own backup plan for. MIT News
For more interesting health developments, check out how coffee may be safer for your heart than you think or the surprising history behind Vitamin C and the common cold. We’ve also got a fascinating piece on how depression might one day be detected in a blood test.